
Peptic Ulcers: Symptoms, Causes, and Treatment in Conyers, GA
A burning ache in your upper stomach that flares up between meals, or wakes you up at night, isn’t something to just push through with antacids for months on end. That kind of pain is one of the most common signs of a peptic ulcer, and while it’s a genuinely uncomfortable condition, it’s also one of the most treatable problems in gastroenterology once you know what’s actually causing it.
Understanding Gas and Bloating
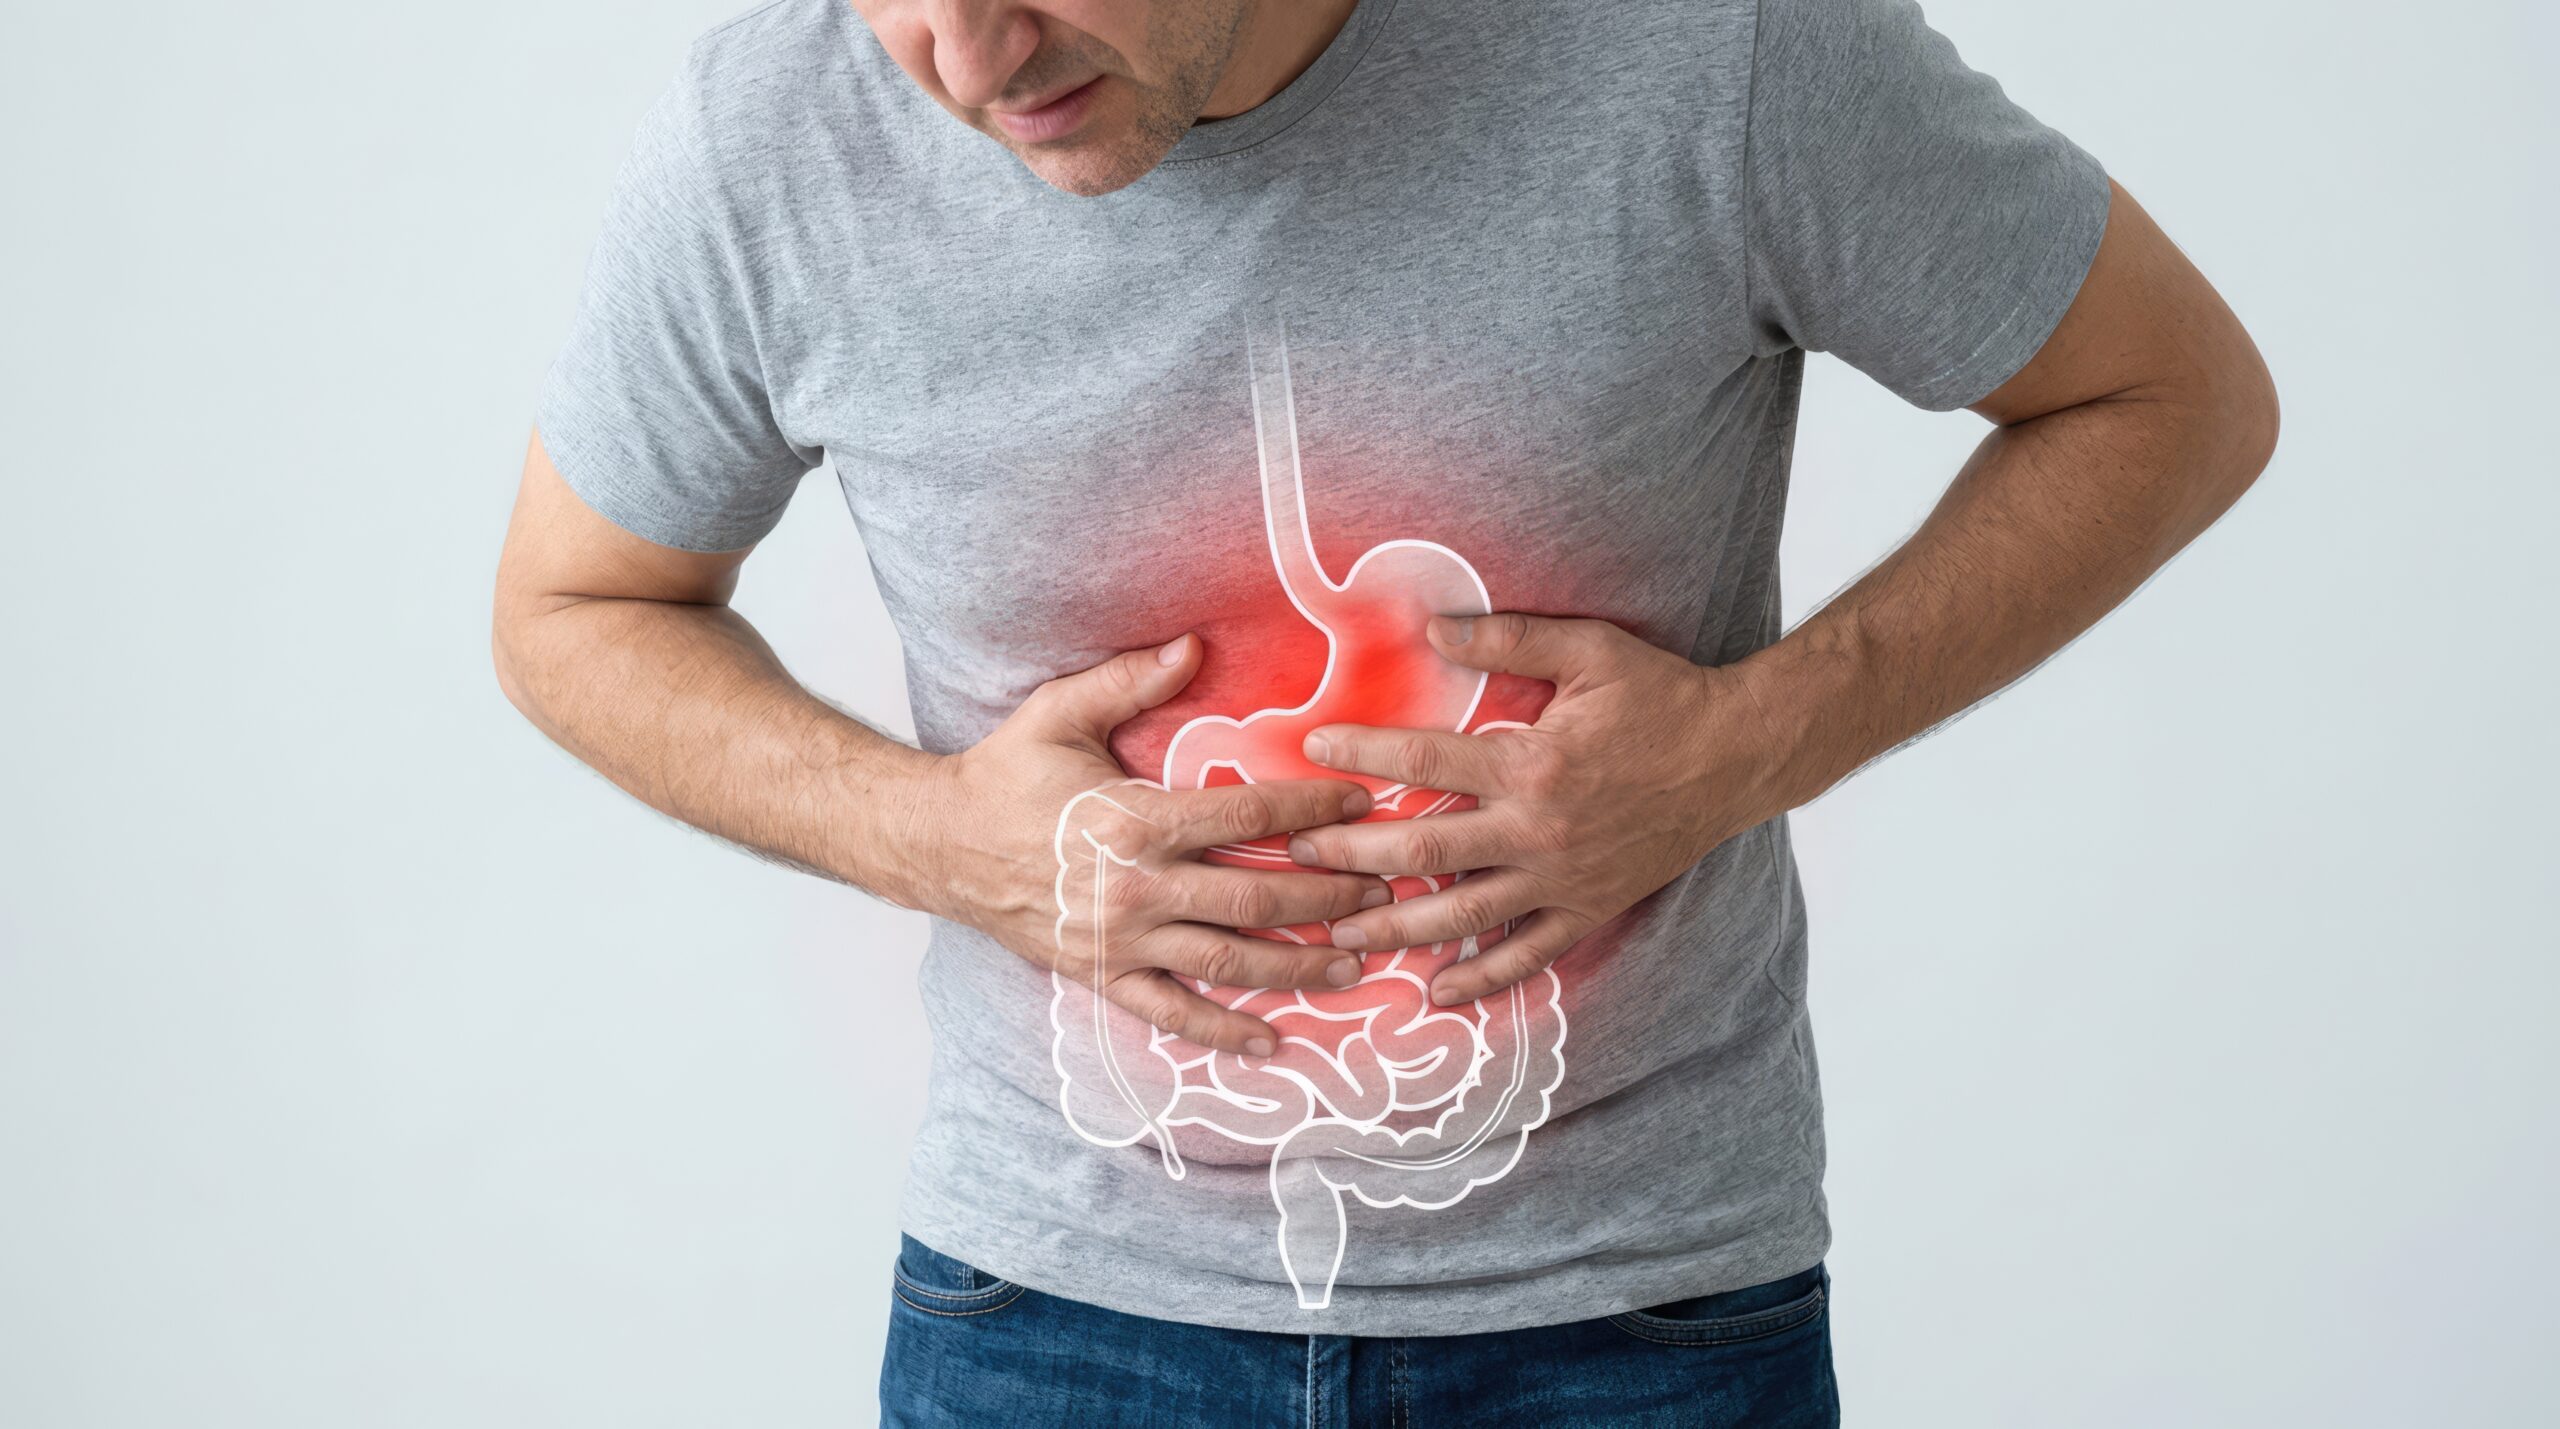
What Is a Peptic Ulcer?
A peptic ulcer is an open sore that forms on the inner lining of your stomach or the upper part of your small intestine. Your digestive tract is normally protected by a thick layer of mucus that shields it from stomach acid. When that mucus layer gets worn down, either because acid production increases or the protective coating breaks down, the acid starts eating into the tissue underneath. That raw, eroded spot is the ulcer itself.
Doctors classify peptic ulcers by where they show up:
Gastric ulcers form inside the stomach itself.
Duodenal ulcers form in the duodenum, the first section of the small intestine right after the stomach.
You can have one or the other, or both at the same time, and you can develop new ulcers more than once over your lifetime even after a previous one has fully healed.
Gastric Ulcer vs. Duodenal Ulcer: Does It Matter Which One You Have?
It matters more than most patients expect. Both types cause similar pain, but the timing often differs in a useful way. With a duodenal ulcer, pain tends to ease right after eating, since food temporarily buffers the acid, then returns two to three hours later once the stomach empties. Gastric ulcers tend to work the other way, with pain that often gets worse shortly after a meal rather than better.
Duodenal ulcers are more common overall and are more strongly linked to H. pylori infection. Gastric ulcers are somewhat more likely to be tied to long-term NSAID use, and because a small percentage of stomach ulcers can be linked to gastric cancer, they’re more likely to need a follow-up endoscopy after treatment just to confirm the area has fully healed. Neither type is something to self-diagnose based on symptom timing alone.
Peptic Ulcer Symptoms
A lot of people with peptic ulcers don’t have any symptoms at all until the ulcer is fairly advanced or starts bleeding. When symptoms do show up, the most common ones include:
- Dull, gnawing, or burning pain in the upper abdomen, often described as feeling like hunger pangs
- Pain that improves or worsens with food (see above), and tends to flare at night
- Bloating or an uncomfortable feeling of fullness
- Frequent burping
- Nausea
- Heartburn that doesn’t fully resolve with over-the-counter antacids
If an ulcer starts bleeding, the symptoms shift and become more serious:
- Vomit that looks red or has a coffee-ground appearance
- Stools that are black, tarry, or maroon-colored
- Sudden dizziness, lightheadedness, or fainting
- Unusual fatigue that doesn’t have another obvious explanation
What Causes Peptic Ulcers
For decades, doctors assumed stress and spicy food were the main culprits behind stomach ulcers. That turned out to be mostly wrong. Stress and spicy food can absolutely make an existing ulcer feel worse, but they don’t cause one to form in the first place. The two real drivers are:
H. pylori infection. Helicobacter pylori is a common bacterium that lives in the mucous lining of the stomach. In a lot of people it causes no problems whatsoever, but in others it triggers ongoing inflammation that wears down the protective lining over time. Nobody fully understands exactly how it spreads person to person, though close contact and contaminated food or water are both suspected routes. It’s far more common than most patients realize.
Long-term NSAID use. Regularly taking pain relievers like ibuprofen, naproxen, or aspirin, especially at higher doses or over an extended stretch, irritates and gradually breaks down the stomach lining. This is one of the most common causes of gastric ulcers in older adults who take daily pain medication for arthritis or chronic pain.
H. Pylori Testing and Ulcer Diagnosis
There isn’t one single test that confirms a peptic ulcer on the spot. Diagnosis usually combines your symptom history with one or more of the following:
H. pylori testing. This can be done through a blood test, a stool sample, or a breath test, where you swallow a specific substance and then breathe into a collection bag to see how your body processes it. If you’ve recently taken antibiotics or antacids, mention that beforehand, since both can throw off the results temporarily.
Upper endoscopy. This is the most direct way to actually see an ulcer. A thin, flexible scope with a small camera is passed down through the throat into the esophagus, stomach, and duodenum. If an ulcer is found, a small tissue sample can be taken during the same procedure to test for H. pylori or rule out anything more concerning. We perform upper endoscopies regularly at our Conyers Clinic, and most patients are surprised by how quick and well-tolerated the procedure actually is.
Peptic Ulcer Treatment
The right treatment depends heavily on what’s causing the ulcer in the first place, which is exactly why testing matters before jumping straight to medication.
Antibiotics for H. pylori. If testing comes back positive, treatment typically involves a combination of two or more antibiotics taken together, since single-antibiotic treatment has a much higher failure rate with this particular bacterium.
Acid-reducing medication. Proton pump inhibitors are the most commonly prescribed option and work by significantly reducing acid production, which gives the ulcer room to heal. H2 blockers work through a different mechanism to reduce acid and are sometimes used as well, either alongside or instead of a PPI depending on the situation.
Stopping or switching pain relievers. If NSAIDs are the culprit, switching to a different pain management approach, sometimes as simple as switching to acetaminophen, is often part of the plan.
Most peptic ulcers heal within a few weeks of starting the right treatment. Ulcers that don’t heal on schedule are called refractory ulcers, and they usually point to one of a few things: the medication regimen wasn’t followed exactly as prescribed, the H. pylori strain is resistant to the antibiotics used, or NSAID use continued during treatment without the doctor knowing. In rare cases, a non-healing ulcer needs a closer look to rule out something else entirely.
Find Relief from Peptic Ulcers
Peptic ulcers respond well to treatment, but only when the underlying cause is actually identified rather than just managed with antacids indefinitely. Dr. Shakoor and the team at CDH combine H. pylori testing, endoscopy when needed, and a treatment plan built around your specific cause and symptom pattern. Our practice, along with the affiliated Eastside Endoscopy Center, holds Joint Commission accreditation, the same standard used to evaluate major hospital systems.
At CDH, we’re committed to your well-being. Let us help you manage peptic ulcers with comprehensive care and expert guidance.

For Life-Threatening Emergencies Call 911
Our location
Colon & Digestive Health Specialists 1805 Honey Creek Commons, Ste B, Conyers GA 30013